Palliative and Supportive Care for Mesothelioma Patients
Understanding Palliative and Supportive Care
Hearing “palliative care” can sound like giving up on treatment, but it is not: this care runs alongside curative treatments, and a randomized trial in people with mesothelioma found that bringing in specialist palliative care early improved quality of life. This page explains what the care covers: pain relief matched to the type of pain, breathlessness help through draining fluid, pleurodesis, oxygen, and morphine, management of side effects such as constipation and nausea, and emotional, spiritual, and family support. It also names who delivers each part, from oncologists and palliative care specialists to social workers and chaplains, so you know who to ask for what.
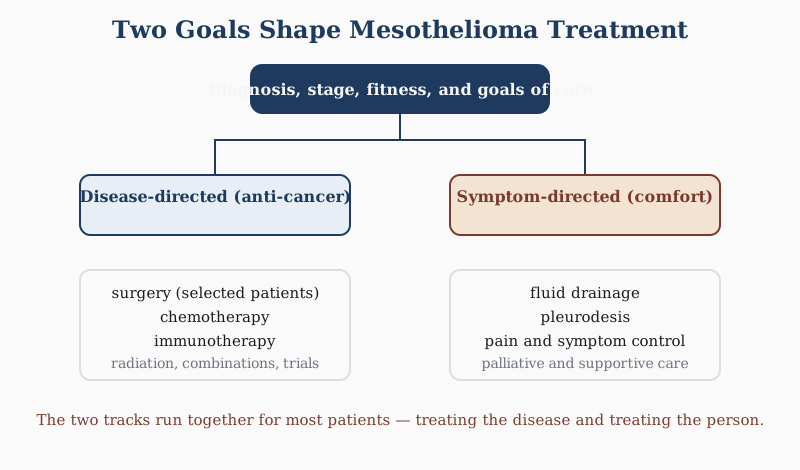
Palliative care focuses on alleviating pain, managing breathlessness, and addressing the emotional and psychological impact of the disease. The right approach can make a significant difference in ensuring that patients feel as comfortable and supported as possible (NCI; for the trial evidence that early palliative care improves quality of life in mesothelioma, see Thorax).
Managing Pain in Mesothelioma
Pain in mesothelioma can vary based on the location of the tumor. Different types of pain require different strategies for relief:
- Visceral pain (from lung invasion) feels deep and diffused.
- Somatic pain (from chest wall invasion) is localized and sharp.
- Neuropathic pain (from intercostal nerve or vertebral invasion) often presents as burning or shooting pain.
Each of these pain types requires a tailored approach. Here’s how medical professionals typically manage them:
- Opioids (such as morphine) are the cornerstone of mesothelioma pain management. They are particularly effective for visceral pain.
- Non-steroidal anti-inflammatory drugs (NSAIDs) like naproxen can help with somatic pain.
- Anticonvulsants (e.g., carbamazepine or gabapentin) are used for neuropathic pain.
- Alternative opioids such as methadone or fentanyl can be considered if a patient does not tolerate morphine well.
The key takeaway? There is no need for mesothelioma patients to endure uncontrolled pain. Pain management should be aggressive, proactive, and tailored to the individual.
Addressing Breathlessness and Respiratory Distress
Breathlessness (dyspnea) is one of the most distressing symptoms of mesothelioma, often worsening as the disease progresses. It can result from pleural effusion (fluid accumulation around the lungs) or tumor growth restricting lung expansion.
Here’s what can be done to help:
- Pleural aspiration – If breathlessness is caused by pleural effusion, removing the excess fluid via aspiration can provide significant relief.
- Talc pleurodesis – This procedure helps prevent fluid reaccumulation, reducing the need for repeated aspirations (NCI).
- Oxygen therapy – While not always effective, some patients benefit from supplemental oxygen.
- Opioids for dyspnea – Morphine is not only a pain reliever but also helps alleviate breathlessness by reducing the brain’s perception of respiratory distress.
Breathlessness can also trigger anxiety, so managing emotional distress is just as important as treating the physical symptoms.
The Role of Psychological and Emotional Support
A mesothelioma diagnosis brings with it a range of emotions—fear, anxiety, grief, and uncertainty. This is why psychological and emotional support must be an integral part of patient care.
Key elements of emotional support include:
- Counseling and therapy – Speaking with a psychologist or counselor can help patients process their emotions and fears.
- Support groups – Connecting with others facing the same challenges can provide comfort and practical advice.
- Spiritual support – Many patients find strength in their faith or spirituality, and chaplains or religious counselors can be invaluable.
Patients should be encouraged to express their concerns and fears so they can receive the support they need.
Special Considerations in Mesothelioma Care
Mesothelioma often brings pressures that go beyond symptom control alone. Many patients live with years of anxiety after known asbestos exposure, and some families are also dealing with questions about work history, benefits, or compensation while trying to make care decisions.
That is why team support matters so much. In practice, it helps when patients and families understand the purpose of each next step:
- Diagnostic procedures help confirm the disease.
- Staging tests help clarify prognosis and treatment options.
- Symptom-relief procedures are meant to improve comfort, even when they are not curative.
Keeping those goals clear can make complex care discussions easier to follow.
Managing Side Effects of Palliative Treatment
While palliative treatments aim to relieve symptoms, they can sometimes introduce side effects. It’s important to anticipate and manage these effects effectively:
- Constipation – A common side effect of opioid painkillers. This can be managed with laxatives and dietary adjustments.
- Nausea and vomiting – Often treated with antiemetic medications such as ondansetron or metoclopramide.
- Fatigue – Patients should balance activity with rest and consider nutritional support to combat weakness.
By proactively addressing side effects, patients can maintain the best possible quality of life.
Educating Patients and Families
Many patients and their families have concerns about symptom control and pain management. Unfortunately, misunderstandings about opioids and palliative care often lead to unnecessary suffering.
Clear communication is essential:
- Explain pain management strategies so patients know what to expect.
- Debunk myths about opioid addiction—when used correctly for pain relief, opioids are safe and effective.
- Discuss end-of-life care early so patients and families can make informed decisions (NCI).
Empowering patients with knowledge ensures they receive the best care possible.
The Importance of a Multidisciplinary Approach
No single healthcare provider can address all aspects of palliative care. A multidisciplinary team is essential, including:
- Physicians and oncologists – Overseeing treatment and symptom management.
- Palliative care specialists – Experts in pain and symptom relief.
- Nurses – Providing hands-on care and education.
- Social workers and case managers – Assisting with emotional and logistical challenges, including benefits, records, family support, and care coordination.
- Spiritual advisors – Offering faith-based support for those who seek it.
A team-based approach ensures that every aspect of a patient’s well-being is addressed.
Looking Ahead: Improving Palliative Care for Mesothelioma
Advancements in palliative care continue to improve symptom management and quality of life for mesothelioma patients. Future developments may include:
- New pain management drugs with fewer side effects.
- Non-invasive breathlessness treatments to improve lung function.
- Personalized palliative care plans based on genetic and clinical factors.
While mesothelioma remains a challenging disease, improving palliative care ensures that patients receive compassionate, effective support.
Final Thoughts
Palliative and supportive care for mesothelioma is about much more than just treating symptoms—it’s about helping patients live as comfortably and fully as possible. With proper pain management, respiratory support, emotional care, and a multidisciplinary team, patients can maintain dignity and quality of life throughout their journey.
By taking a proactive approach to symptom control and patient education, healthcare providers can make a significant difference in the lives of those affected by this disease.
Frequently asked questions
Does palliative care mean giving up on treatment?
No. Palliative and supportive care runs alongside other care, not instead of it. The aim is to ease discomfort and lift day-to-day quality of life starting at diagnosis, controlling pain and breathlessness, easing side effects, and supporting the emotional needs of patients and families.
How is mesothelioma pain controlled?
Pain is treated according to its type. Morphine and similar opioids form the cornerstone, non-steroidal anti-inflammatory drugs help with sharp, localized chest-wall pain, and anticonvulsants such as gabapentin or carbamazepine relieve burning or shooting nerve pain. When morphine is not tolerated, alternatives like methadone or fentanyl can be used.
What can be done about breathlessness?
Several things. If fluid around the lung is the cause, draining it through pleural aspiration brings real relief, and talc pleurodesis can stop the fluid from building up again. Some patients benefit from oxygen, and morphine can ease the sensation of breathlessness as well as pain. Anxiety management matters too, since breathlessness and distress feed each other.
Who provides palliative and supportive care?
A multidisciplinary team: physicians and oncologists guiding treatment, palliative care specialists expert in pain and symptom control, nurses who give bedside care and teach, social workers and case managers dealing with logistical and family needs, and spiritual advisors for those who want them. Working together, they cover physical, emotional, and practical needs at once.
Do opioid painkillers cause addiction when used for cancer pain?
Used properly to control cancer pain, these medicines are both safe and effective, and worries about addiction should not keep patients from relief. Misunderstandings about opioids often cause needless suffering, which is why clear conversations about pain management belong early in care.
References
- National Cancer Institute — Palliative Care in Cancer: what palliative care is, when it starts, and what it covers for patients and families.
- Thorax — Early specialist palliative care on quality of life for malignant pleural mesothelioma: a randomised controlled trial: the trial evidence that early palliative involvement improves quality of life.
- National Cancer Institute — Malignant Mesothelioma Treatment (PDQ) Patient Version: official description of pleurodesis, fluid drainage, and symptom-directed treatment.
- National Cancer Institute — Hospice Care: end-of-life care options and what hospice provides.